
IMFINZI in combination with gemcitabine and cisplatin as neoadjuvant treatment, followed by single-agent IMFINZI as adjuvant treatment following RC

EFFICACY

In the treatment of cis-eligible MIBC

What were the event-free survival results demonstrated in the NIAGARA study?

PERIOPERATIVE IMFINZI* + neoadjuvant gem-cis: The FIRST FDA-approved IO-based regimen to significantly improve EFS compared with neoadjuvant gem-cis in patients with MIBC1,2†

EVENT-FREE SURVIVAL (dual primary endpoint)1,3

NIAGARA Study Results Showing a 32% Reduction in Event Risk with the NIAGARA Regimen Versus Neoadjuvant Gemcitabine Plus Cisplatin.

REDUCTION IN RISK OF AN EVENT (progression, recurrence, death, or not undergoing RC)† with the NIAGARA Regimen‡ vs neoadjuvant gem-cis (HR=0.68 [95% CI, 0.56-0.82]; P<0.0001)

Median EFS was not reached with the NIAGARA Regimen‡ (95% CI, NR-NR) vs 46.1 months with neoadjuvant gem-cis (95% CI, 32.2-NR)

Median duration of follow-up: 42.3 months (range: 0.03-61.3).

EVENT-FREE SURVIVAL (dual primary endpoint)1,3

NIAGARA Study EFS Graph Showing Higher 12- and 24- Month Event-Free Survival with the NIAGARA Regimen Versus Neoadjuvant Gemcitabine Plus Cisplatin.
 

SCROLL

  • Approximately 68% of patients treated with the NIAGARA Regimen‡ were estimated to be event free at 2 years3
  • EFS rates at 12 and 24 months were not powered to determine statistical significance3
  • EFS maturity is 39%3

What were the EFS results across patient subgroups?

In the NIAGARA study, EFS data were consistent across most prespecified patient subgroups3

EFS BY PRESPECIFIED PATIENT SUBGROUP (exploratory analysis)1,3

NIAGARA Study Forest Plot Showing EFS Across Prespecified Patient Subgroups.
 

SCROLL

The EFS prespecified patient subgroup analysis was not powered to show differences between or within individual subgroups and was not powered to determine statistical significance.3

*A perioperative regimen consists of both neoadjuvant and adjuvant treatment.1

†Event-free survival was defined as the time from randomization to first recurrence of disease post-RC, time to first documented progression in patients who were precluded from RC, time of expected surgery in patients who refused RC or failure to undergo RC due to residual disease, or death due to any cause, whichever occurs first.3

‡The NIAGARA Regimen is defined as neoadjuvant IMFINZI + gem-cis followed by adjuvant IMFINZI as a single agent after RC.1

pCR RESULTS (dual primary endpoint): PRIMARY ANALYSIS AND EXPLORATORY REANALYSIS3

  • At the primary analysis (data cutoff: January 2022), 33.8% (n=180/533; 95% CI, 29.8-38.0) of patients treated with the NIAGARA Regimen‡ and 25.8% (n=137/530; 95% CI, 22.2-29.8) of patients treated with neoadjuvant gem-cis achieved a pCR
    • pCR rates reported during the primary analysis did not reach statistical significance
  • At the reanalysis (data cutoff: April 2024), 37.3% (n=199/533; 95% CI, 33.2-41.6) of patients treated with the NIAGARA Regimen‡ and 27.5% (n=146/530; 95% CI, 23.8-31.6) of patients treated with neoadjuvant gem-cis achieved a pCR
    • The reanalysis included an additional 59 patients§
    • This analysis was exploratory and not powered to determine statistical significance

§The descriptive reanalysis of pCR included the results of 59 evaluable samples that were omitted from the primary analysis because the date of central assessment (which occurred after January 14, 2022), rather than the date of surgery (which occurred before January 14, 2022), was used as the data cutoff date.

NCCN

CATEGORY 1,

PREFERRED

The first and only NCCN Category 1, Preferred perioperative systemic treatment option for cis-eligible MIBC

Neoadjuvant durvalumab (IMFINZI®) + gemcitabine + cisplatin, followed by cystectomy, then adjuvant durvalumab (IMFINZI®) for cis-eligible MIBC4||

Neoadjuvant durvalumab (IMFINZI®) + gemcitabine + cisplatin, followed by cystectomy, then adjuvant durvalumab (IMFINZI®) for cis-eligible MIBC4||

||See the NCCN Clinical Practice Guidelines in Oncology (NCCN Guidelines®) for detailed recommendations, including other preferred treatment options.4

NCCN=National Comprehensive Cancer Network® (NCCN®).

In the treatment of cis-eligible MIBC

What were the overall survival results demonstrated in the NIAGARA study?

PERIOPERATIVE IMFINZI* + neoadjuvant gem-cis: The FIRST FDA-approved IO-based regimen to achieve superior improvement in OS compared with neoadjuvant gem-cis alone in the curative intent setting of MIBC1,2

OVERALL SURVIVAL (secondary endpoint)1,3

NIAGARA Study Results Showing a 25% Reduction in Risk of Death with the NIAGARA Regimen Versus Neoadjuvant Gemcitabine Plus Cisplatin.

REDUCTION IN RISK OF DEATH with the NIAGARA Regimen† vs neoadjuvant gem-cis (HR=0.75 [95% CI, 0.59-0.93]; P=0.01)

Median OS was not reached with the NIAGARA Regimen† (95% CI, NR-NR) nor with neoadjuvant gem-cis (95% CI, NR-NR)

Fewer deaths were reported with the NIAGARA Regimen† (25.5%; n=136/533) vs neoadjuvant gem-cis (31.9%, n=169/530)1,3

Median duration of follow-up: 46.3 months (range: 0.03-64.7).
The key secondary endpoint was OS as assessed with an alpha-allocation approach, following EFS in the statistical hierarchy.

OVERALL SURVIVAL (secondary endpoint)1,3

NIAGARA Study OS Graph Showing Higher 12- and 24- Month Overall Survival with the NIAGARA Regimen.
 

SCROLL

>82% estimated OS rate at 2 years with the NIAGARA Regimen3†

  • OS rates at 12 and 24 months were not powered to determine statistical significance3
  • OS maturity is 27%3

What were the OS results across patient subgroups?

In the NIAGARA study, OS data were consistent across most prespecified patient subgroups3

OS BY PRESPECIFIED PATIENT SUBGROUP ANALYSIS (exploratory analysis)1,3

Niagara Study Exploratory Analysis of OS Across Prespecified Patient Subgroups.
Overall Survival by Prespecified Patient Subgroup
 

SCROLL

The OS prespecified patient subgroup analysis was not powered to show differences between or within individual subgroups and was not powered for statistical significance.3

Hear what experts say about the NIAGARA Regimen†

Dr Neal Shore and Dr Aleksandra Drakaki discuss their experience with the NIAGARA Regimen†

*A perioperative regimen consists of both neoadjuvant and adjuvant treatment.1

†The NIAGARA Regimen is defined as neoadjuvant IMFINZI + gem-cis followed by adjuvant IMFINZI as a single agent after RC.1

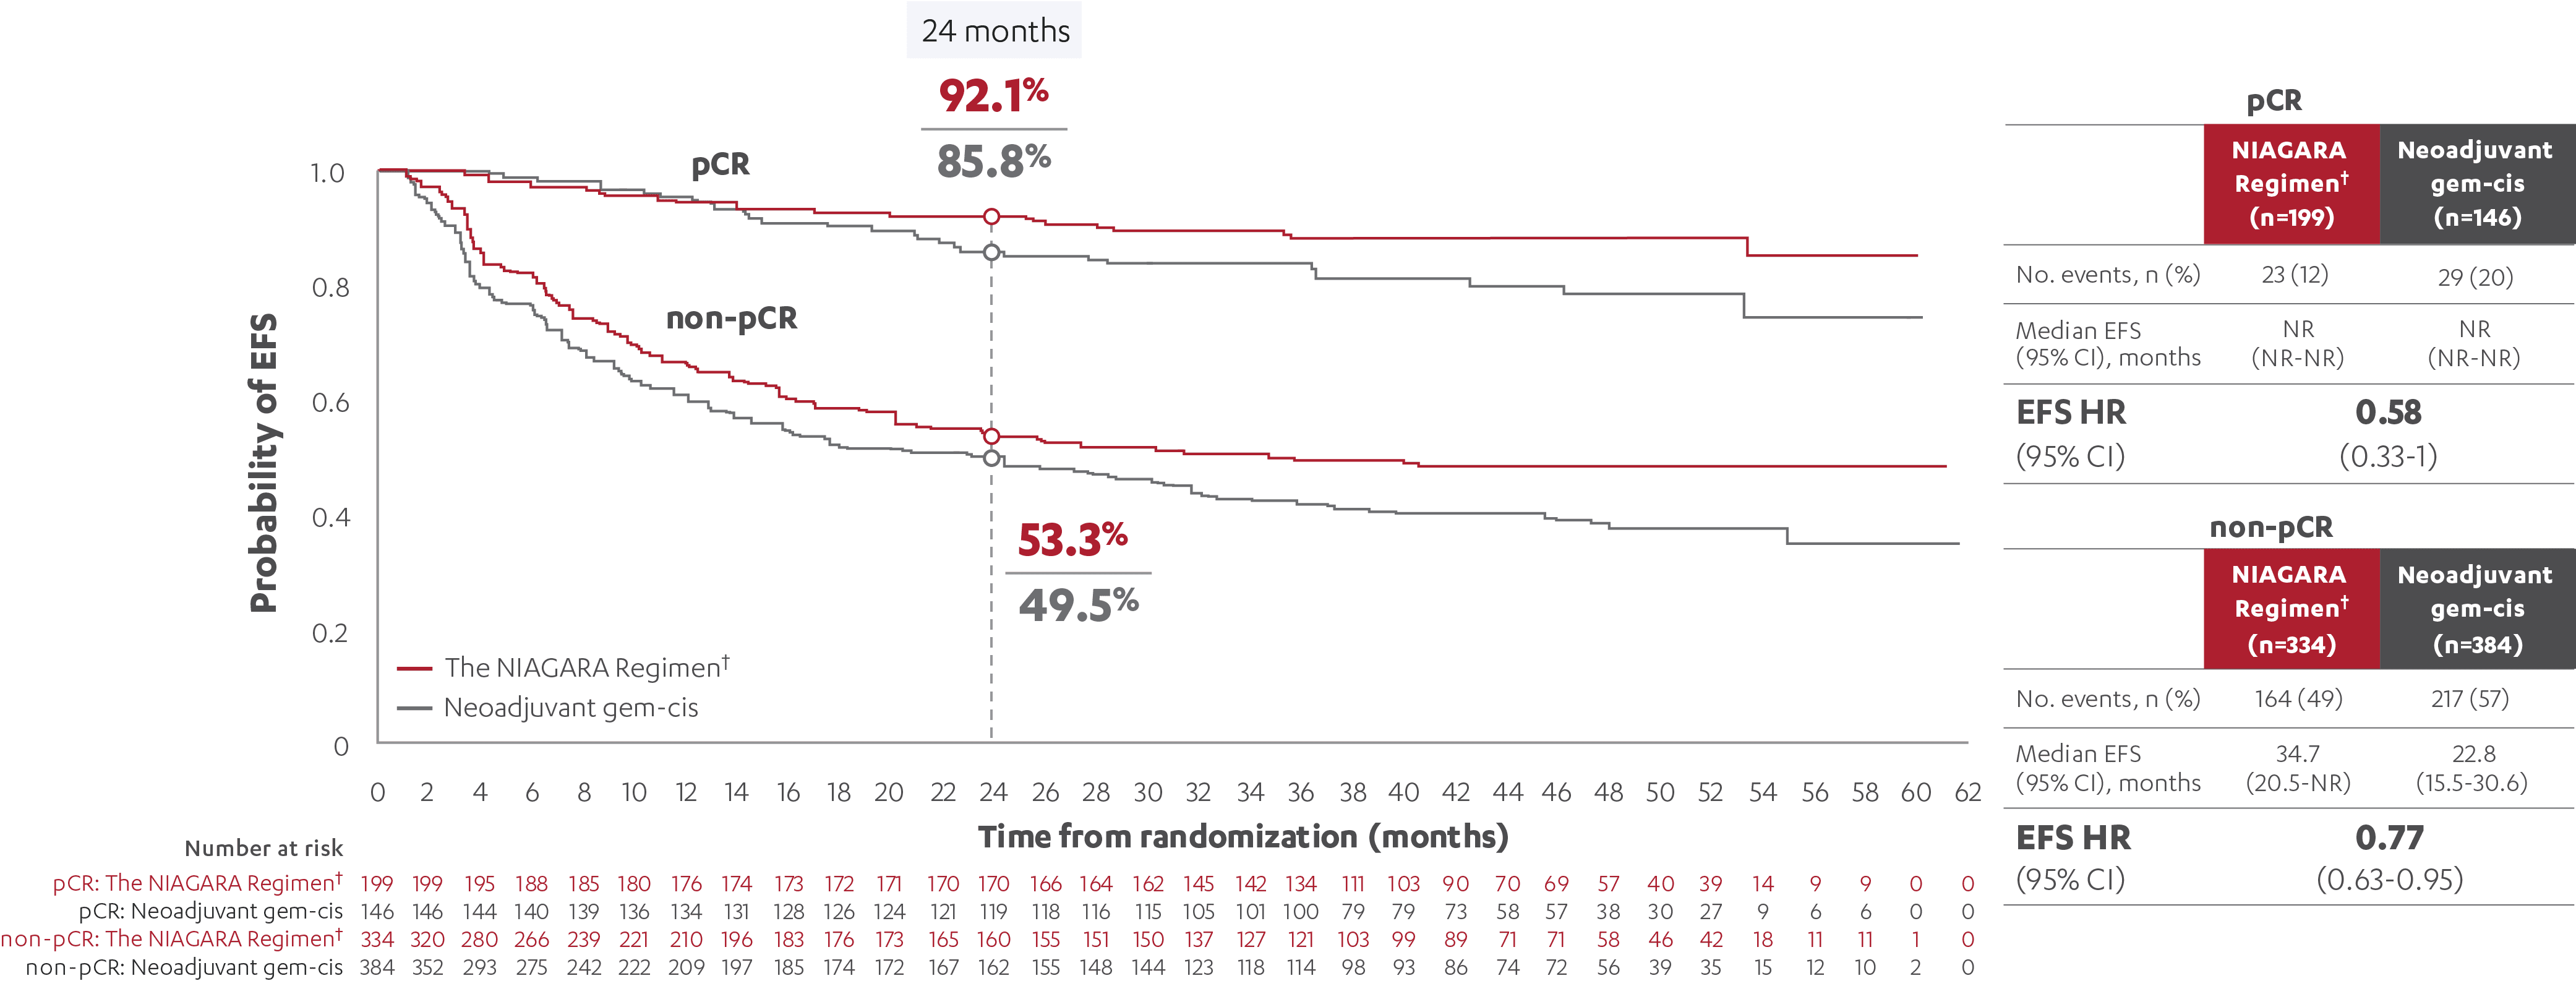
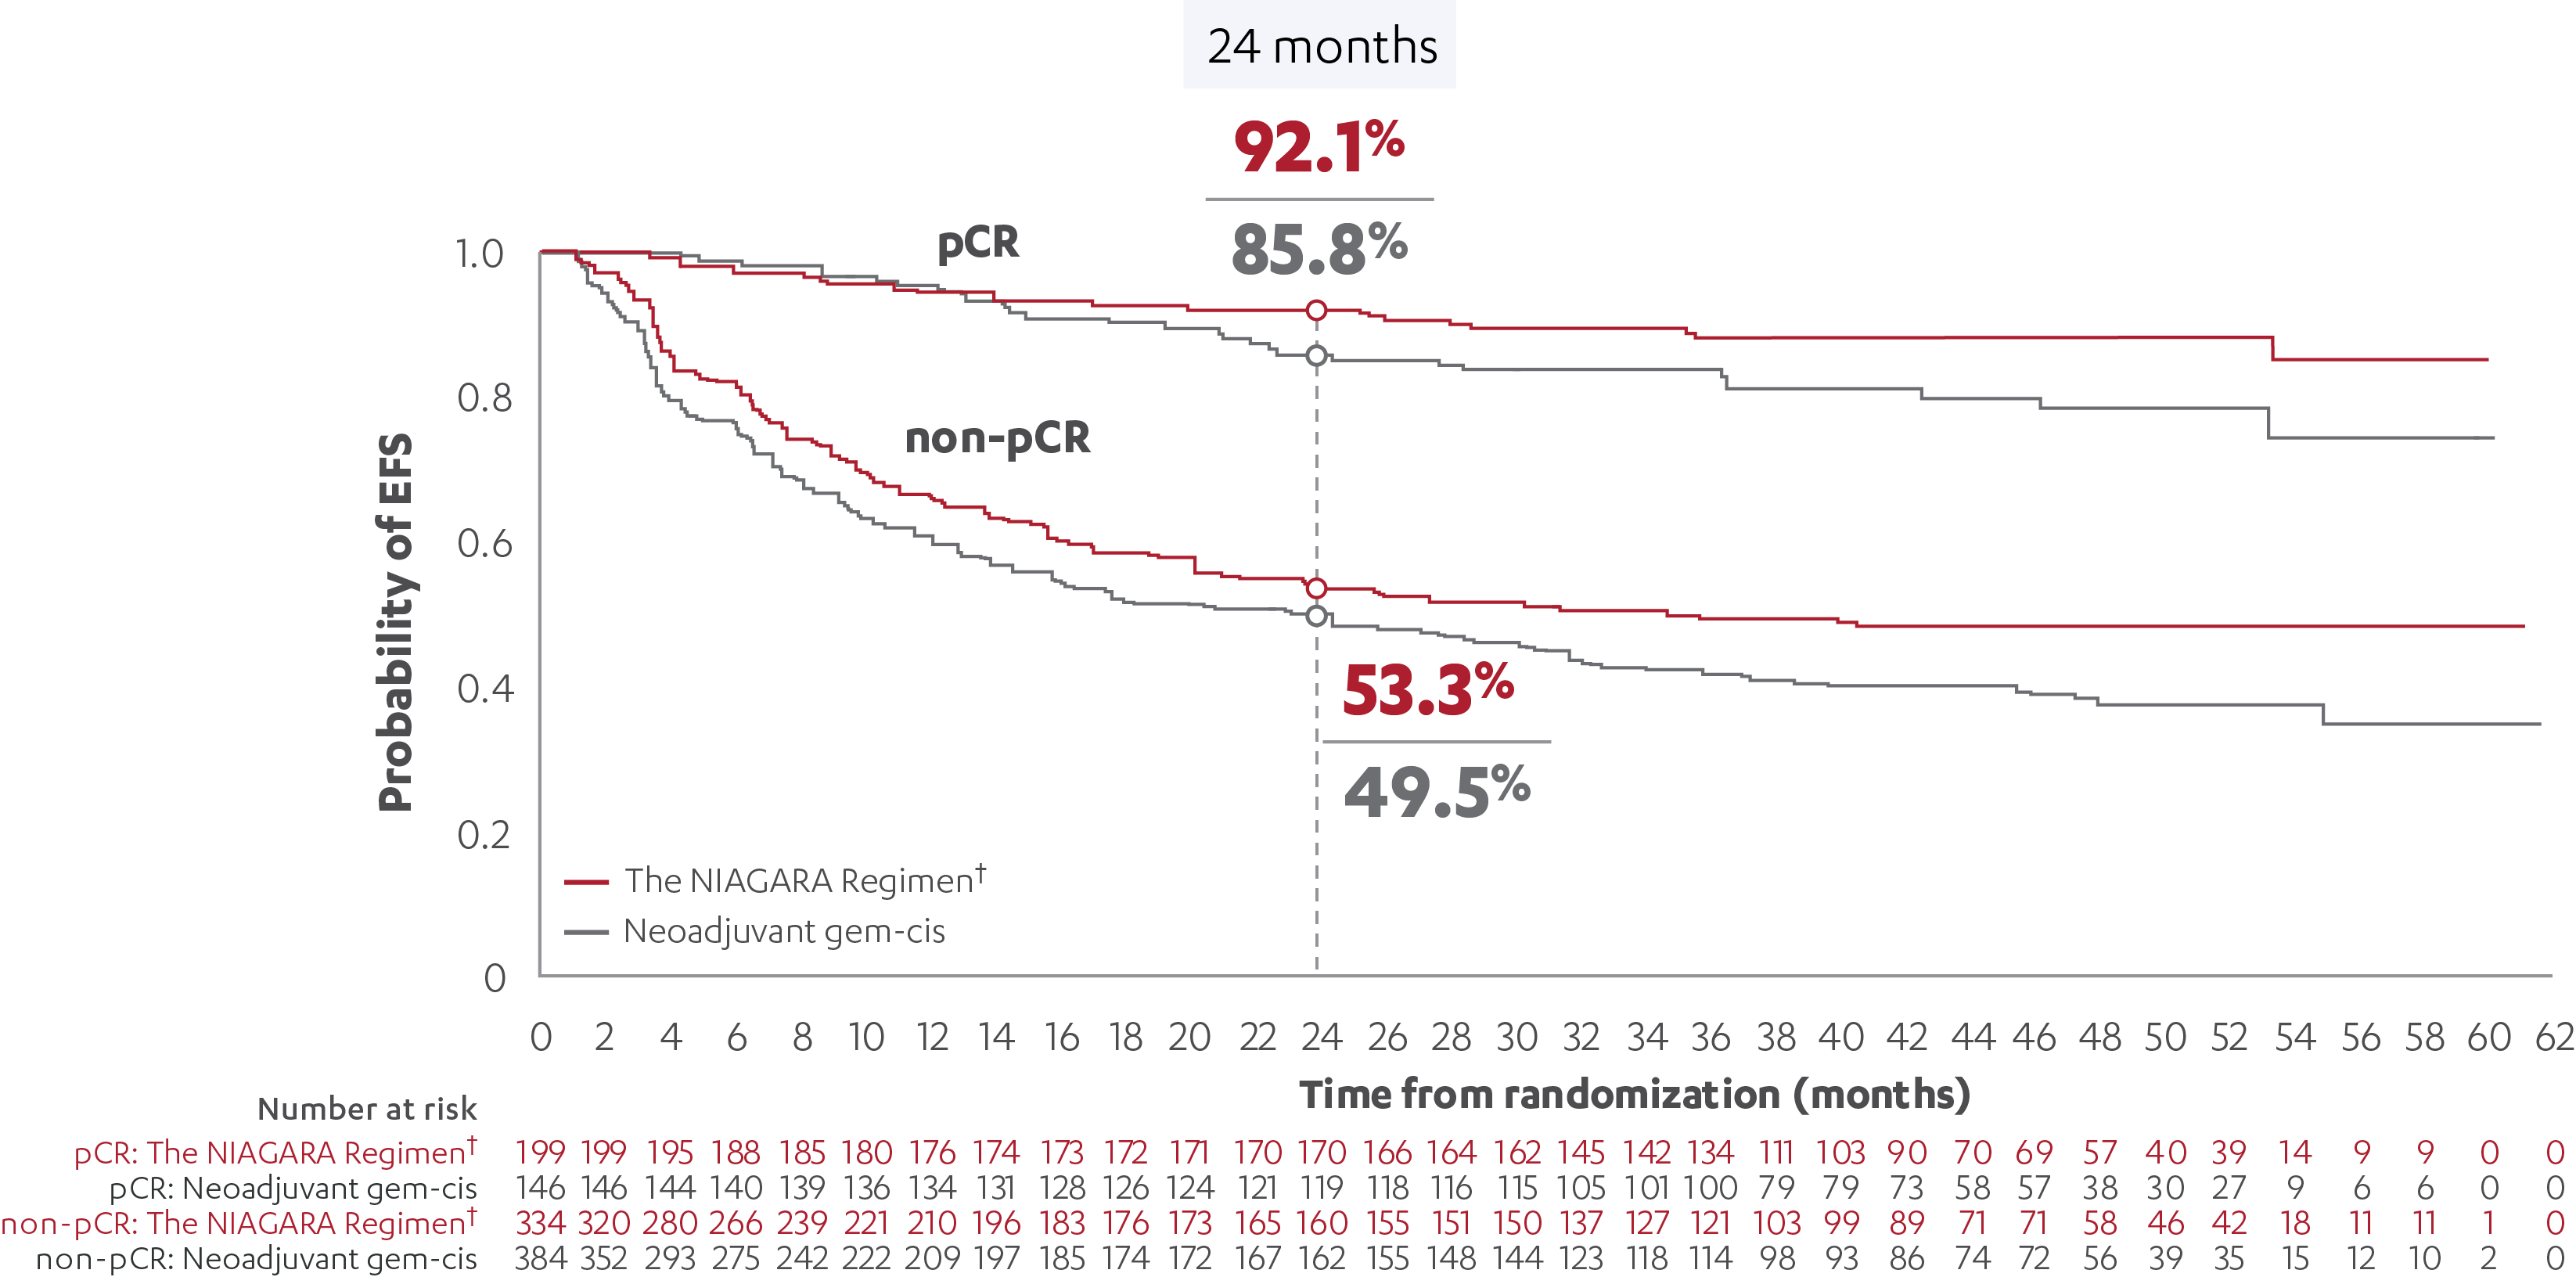
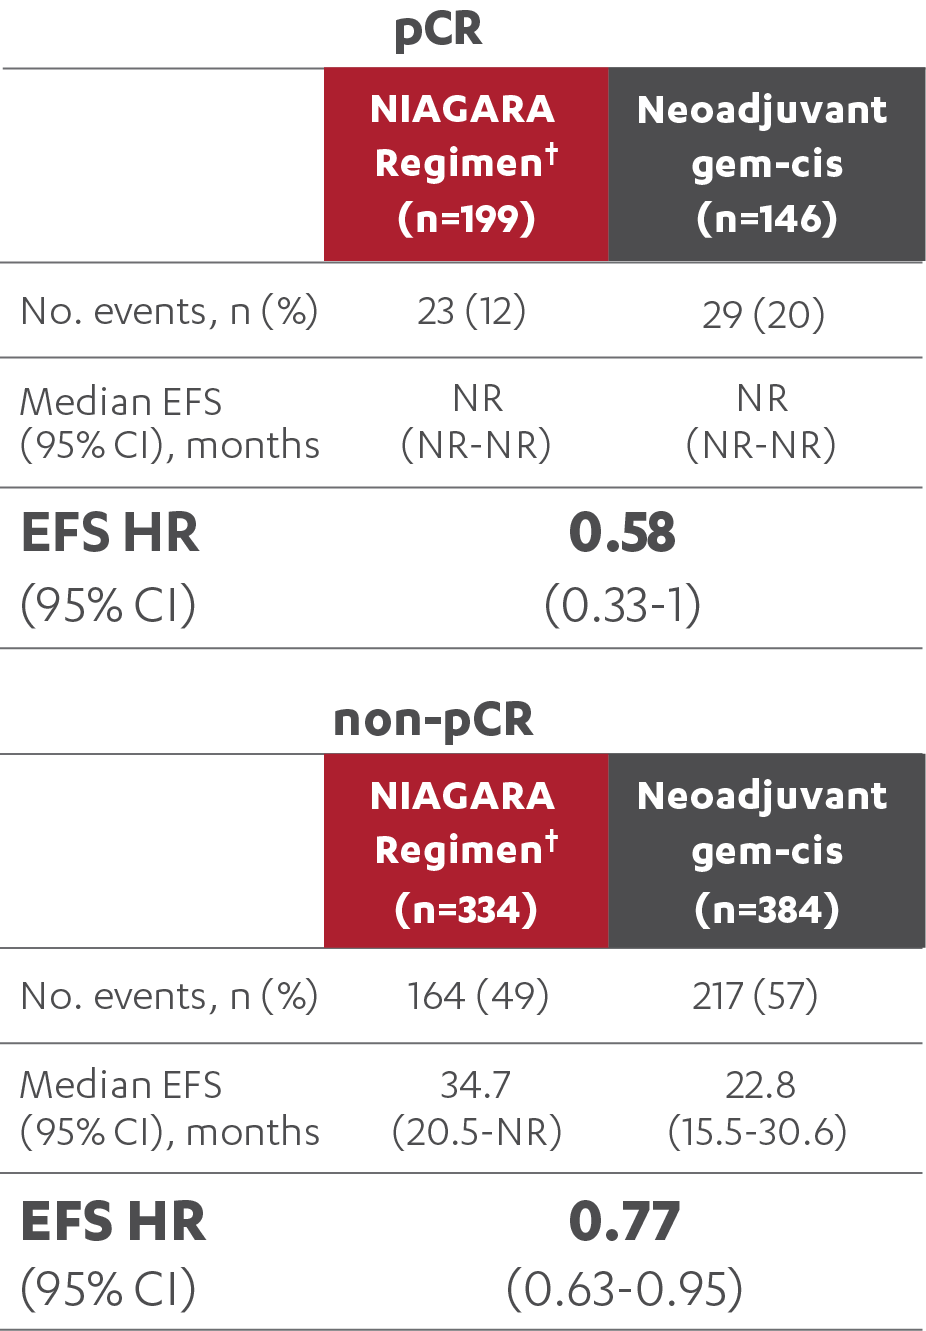
What were the EFS and OS results by pCR status in the NIAGARA study?

EFS* results by pCR status

EFS RESULTS IN PATIENTS WITH AND WITHOUT A pCR (post-hoc analysis)5

NIAGARA Study Post-Hoc Analysis of Event-Free Survival by Pathologic Complete Response Status, Based on an Exploratory pCR Reanalysis.
 

SCROLL

  • For this analysis, pCR status was based on the exploratory reanalysis of pCR3,5‡
  • Post-hoc analysis of EFS by pCR status was not powered to determine statistical significance5
  • Data cutoff was April 29, 20245

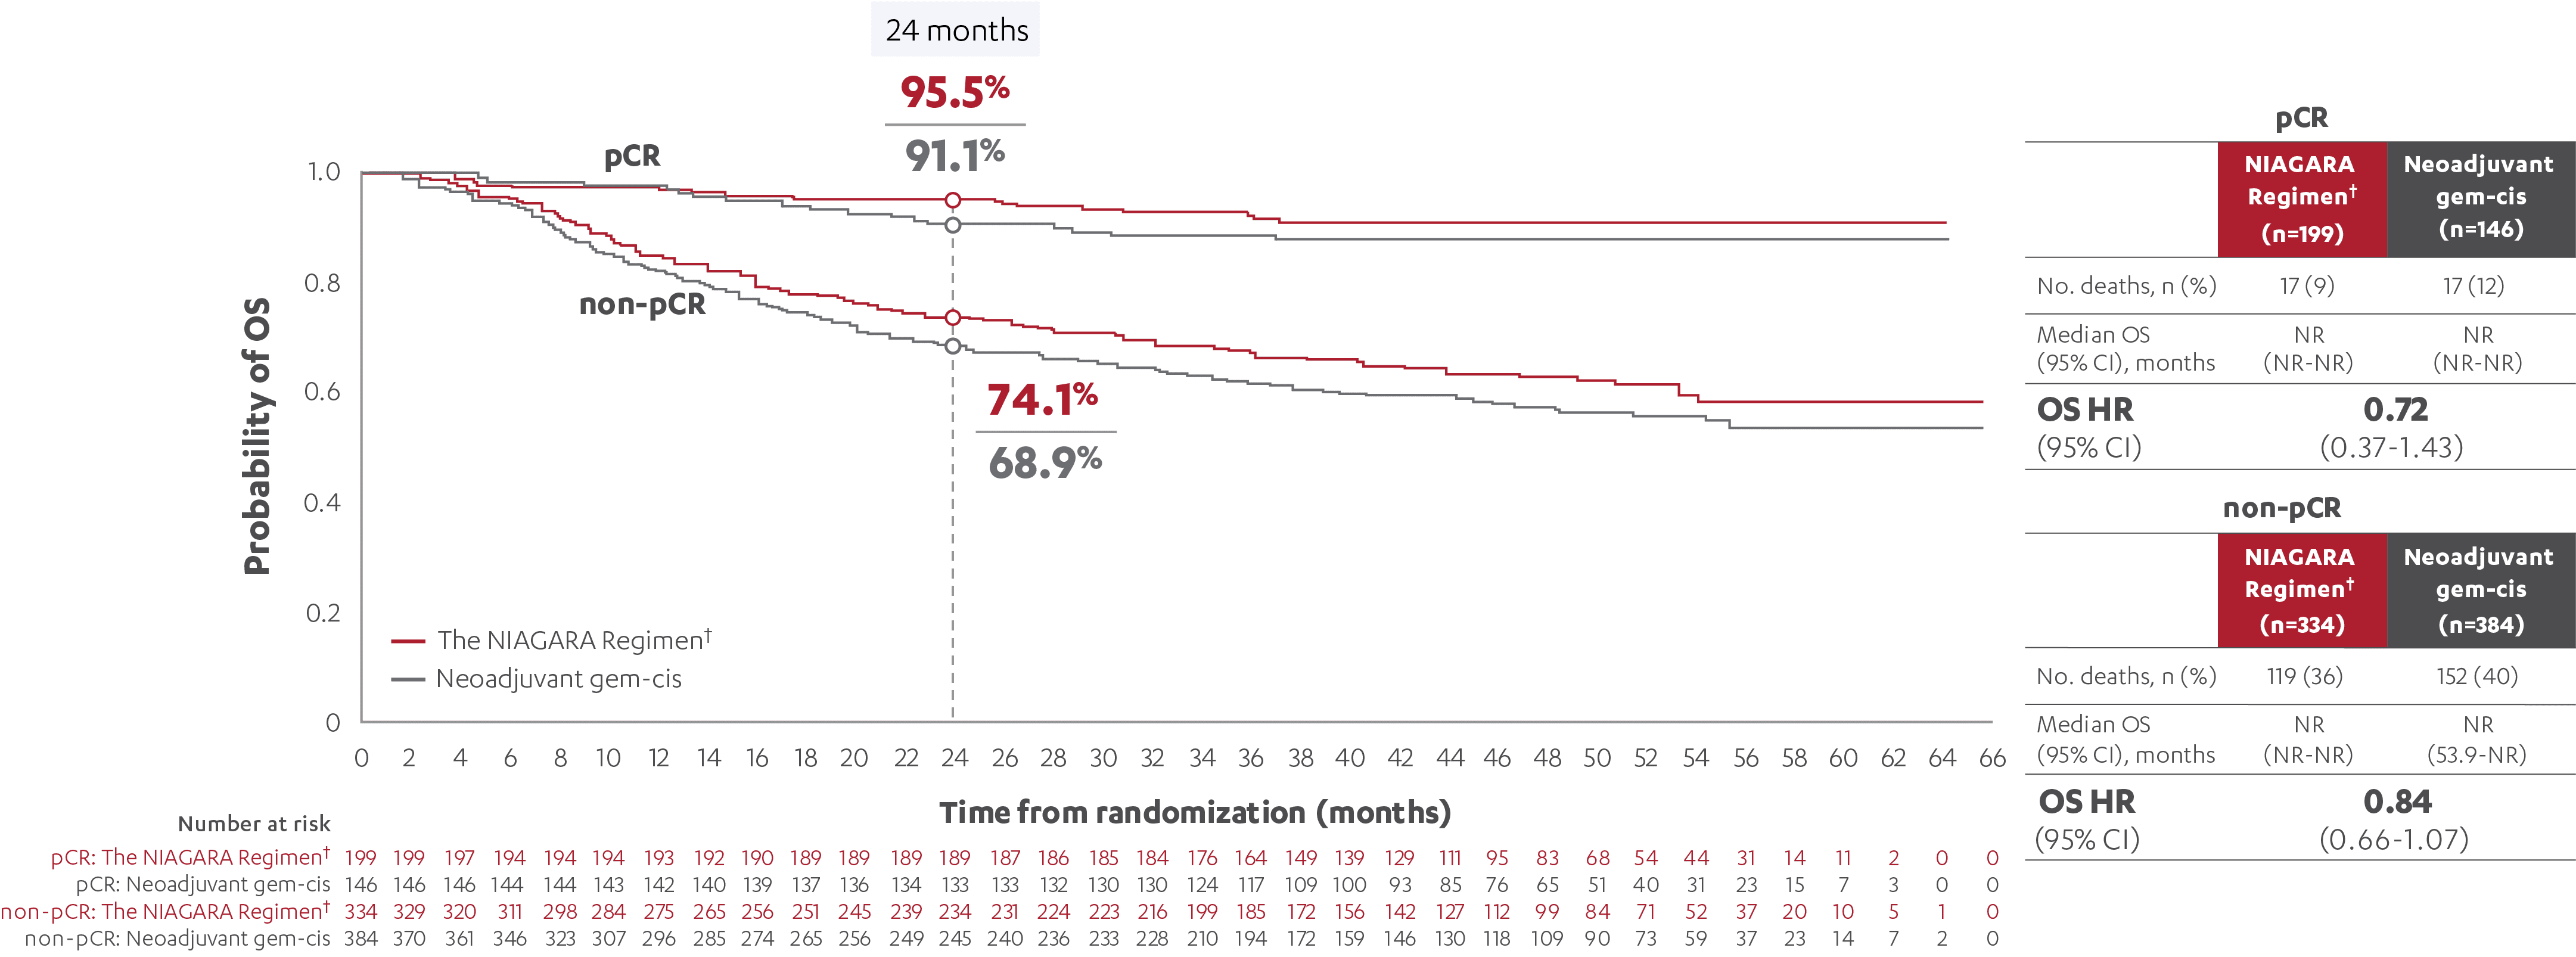
OS results by pCR status

OS RESULTS IN PATIENTS WITH AND WITHOUT A pCR (post-hoc analysis)5

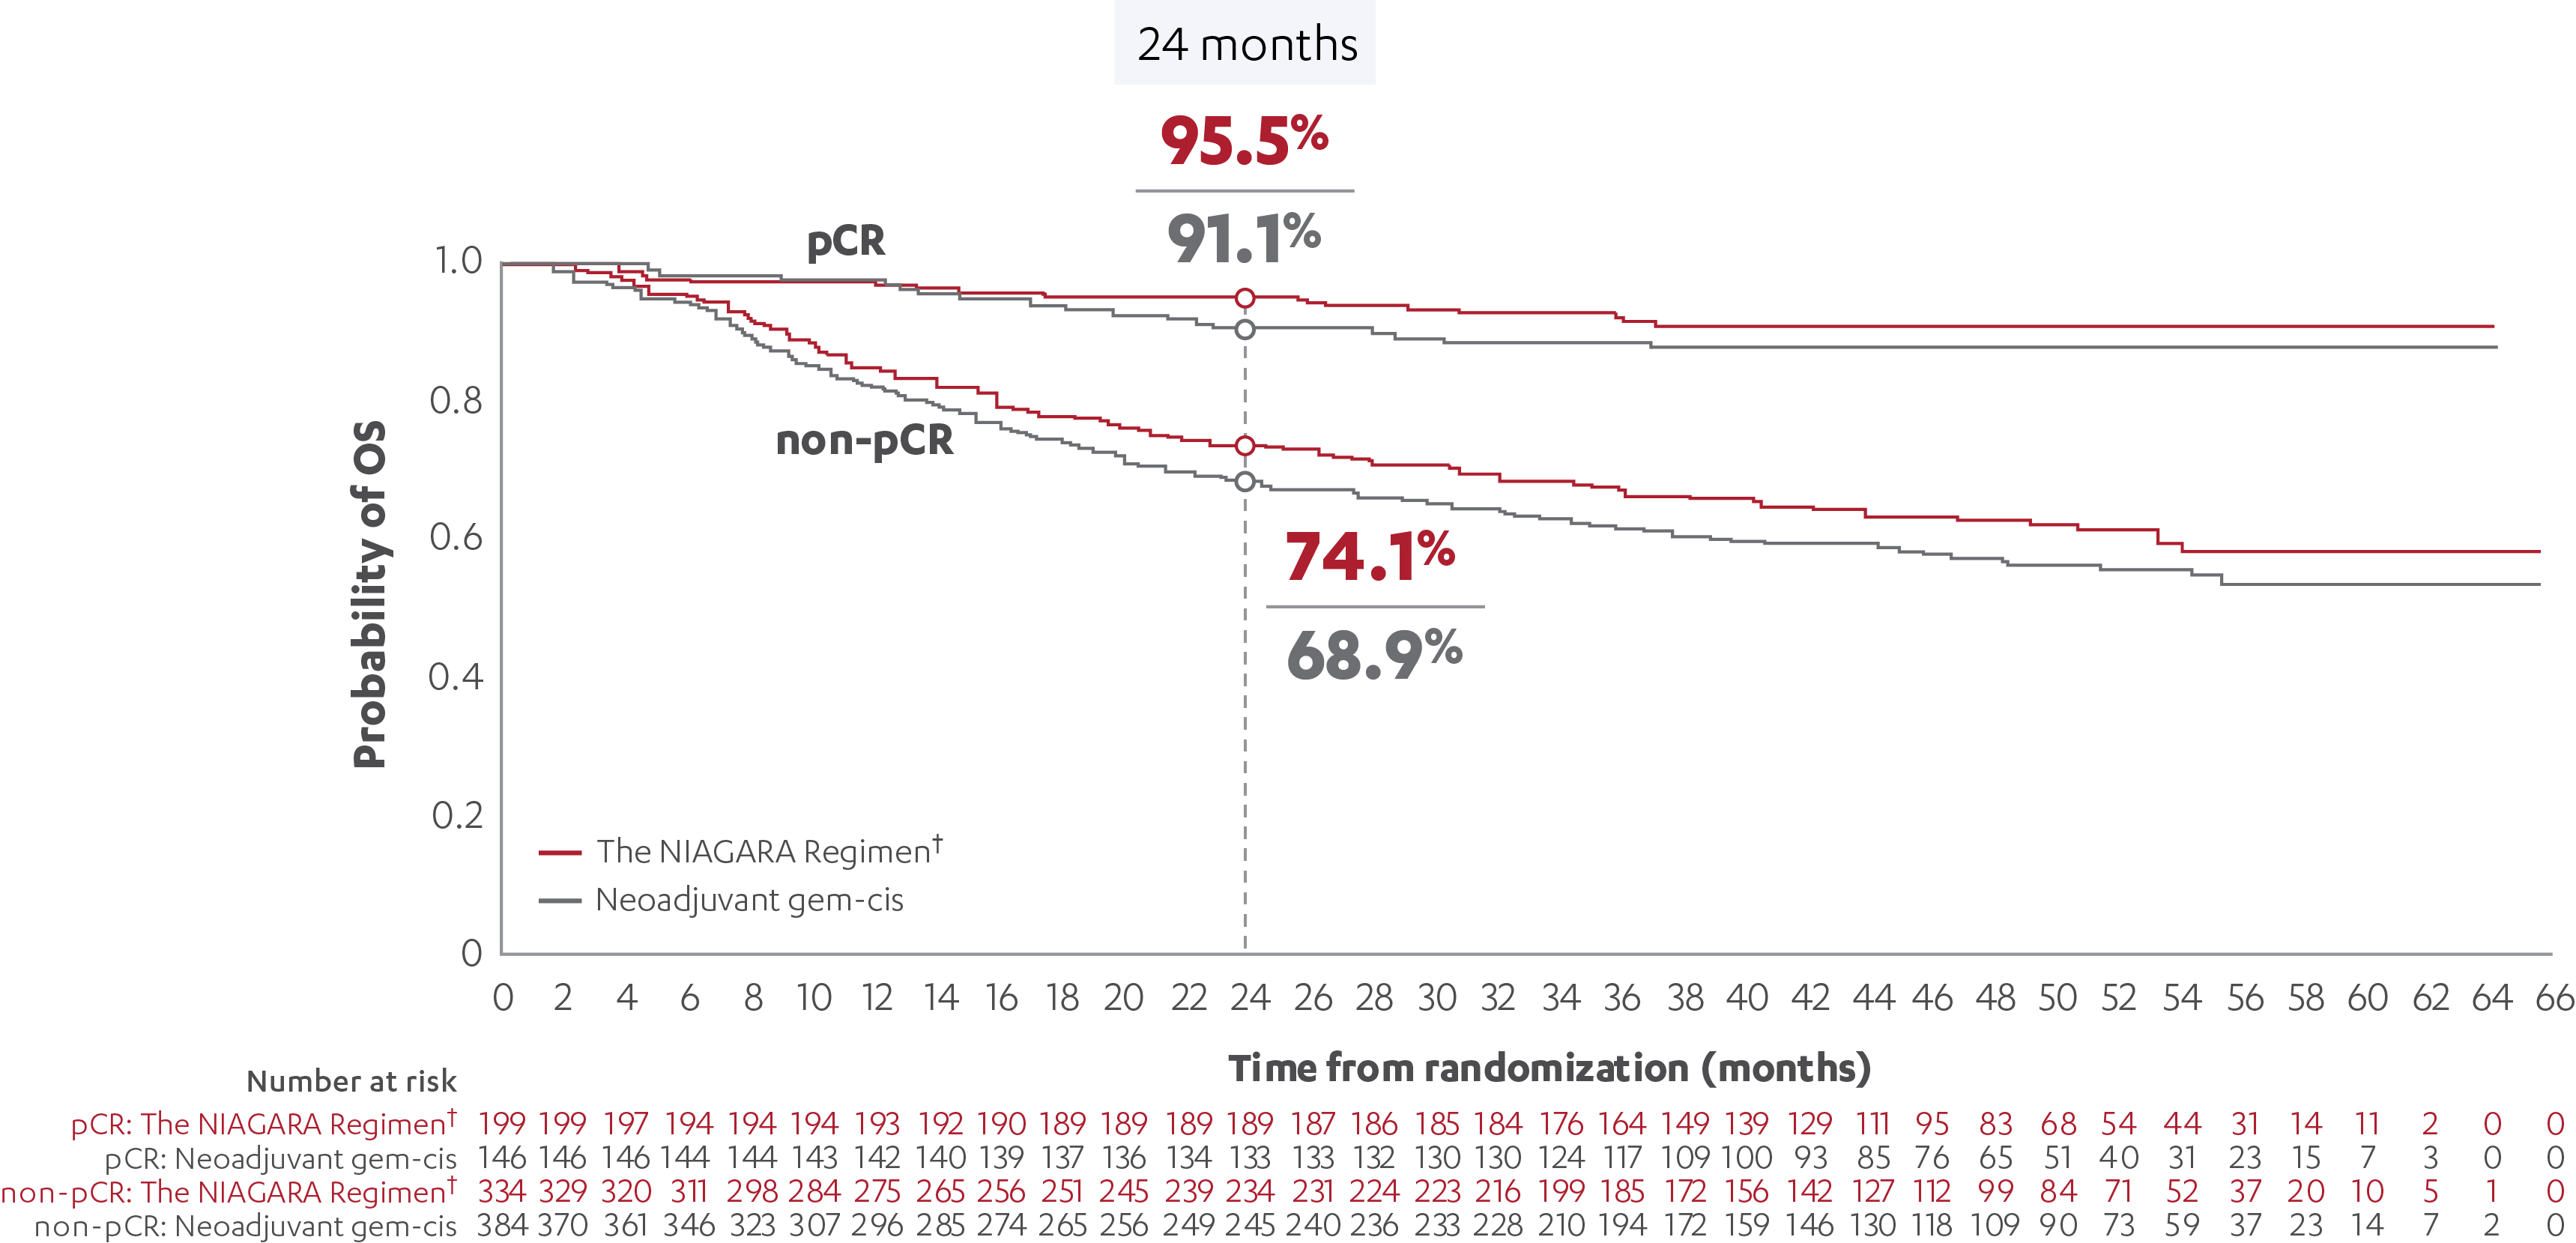
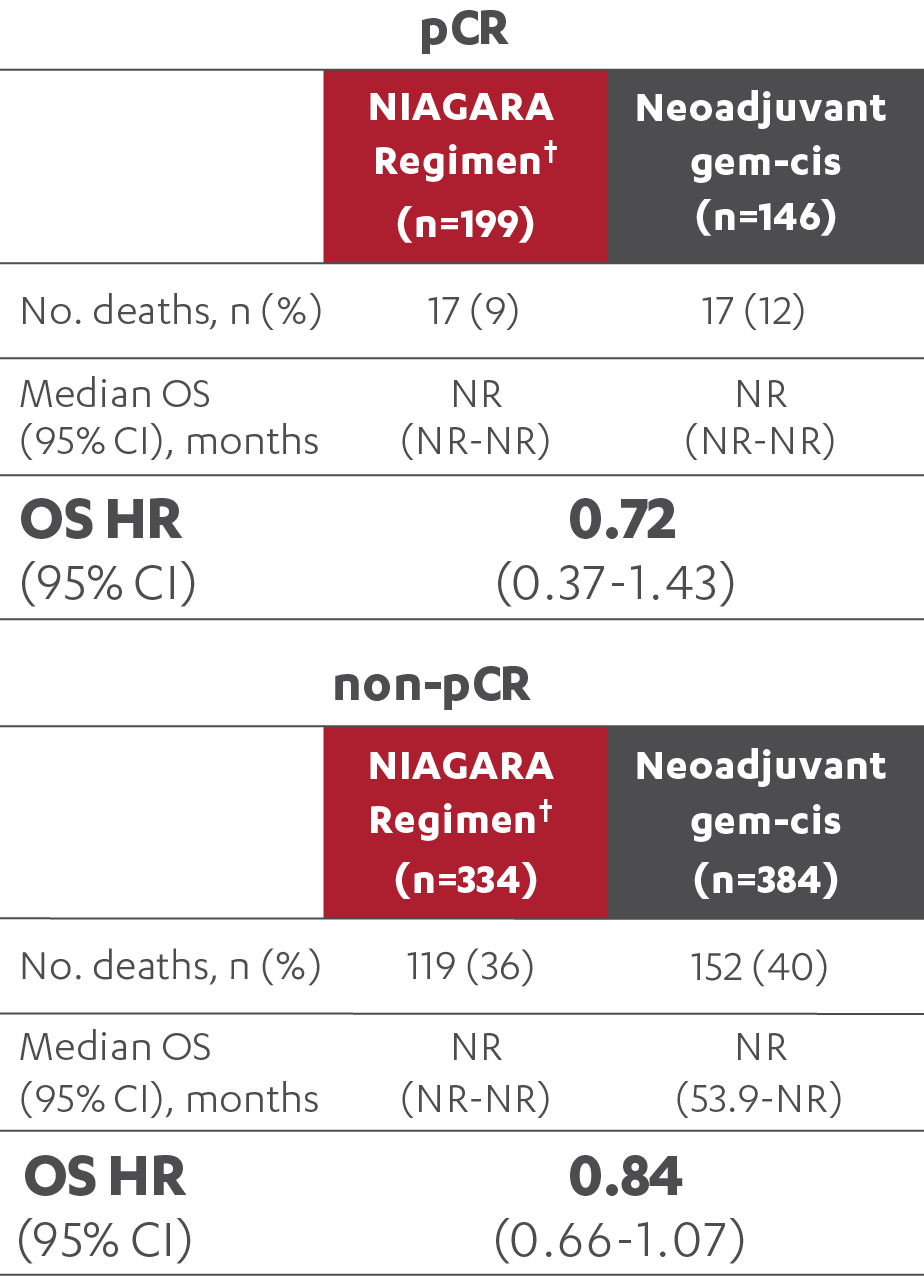
NIAGARA Study OS Analysis Demonstrating Favorable Survival Trends Across pCR and Non-pCR Subgroups.
 

SCROLL

OS in Patients With and Without a pCR
  • For this analysis, pCR status was based on the exploratory reanalysis of pCR3,5‡
  • Post-hoc analysis of OS by pCR status was not powered to determine statistical significance5
  • Data cutoff was April 29, 20245

What were the baseline characteristics in the subgroups of patients with and without a pCR?

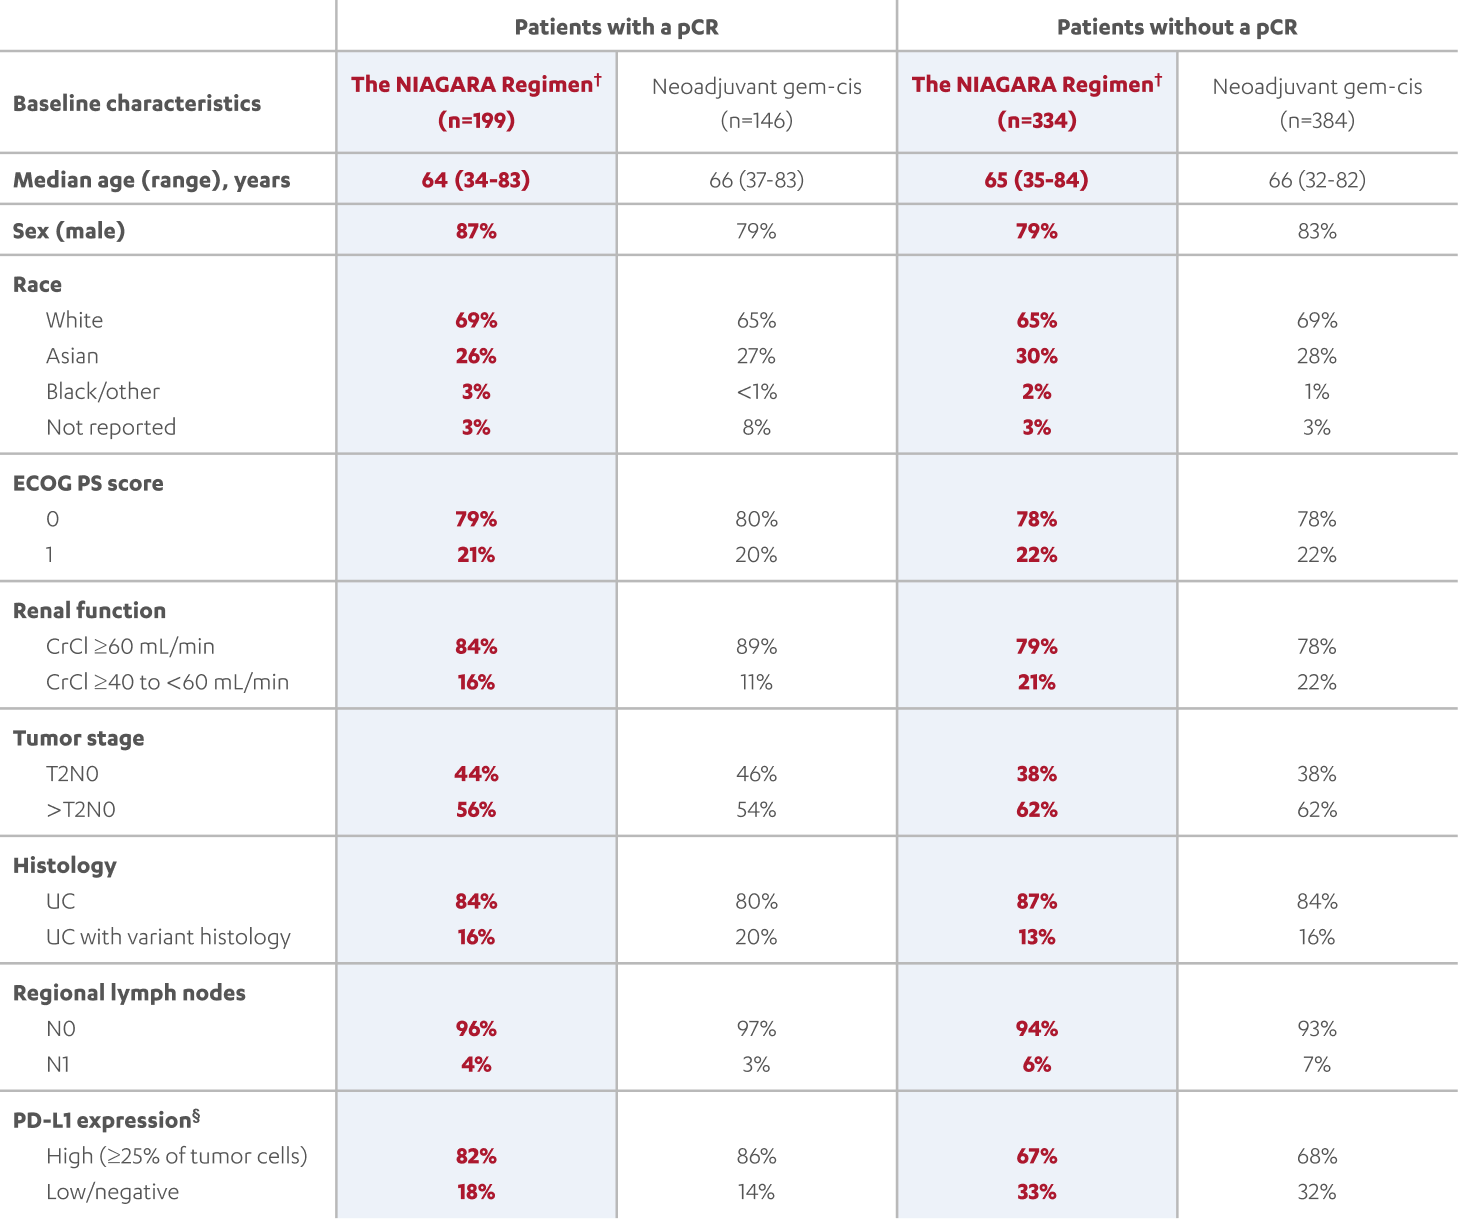
Baseline characteristics were generally well balanced between treatment arms in the subgroups of patients with and without a pCR5

BASELINE CHARACTERISTICS IN PATIENTS WITH AND WITHOUT A pCR (post-hoc analysis)1,3,5

Baseline Characteristics of NIAGARA Study Patients by pCR Outcome and Treatment Group.
Overall Survival by Prespecified Patient Subgroup
 

SCROLL

*Event-free survival was defined as the time from randomization to first recurrence of disease post-RC, time to first documented progression in patients who were precluded from RC, time of expected surgery in patients who refused RC or failure to undergo RC due to residual disease, or death due to any cause, whichever occurs first.3

†The NIAGARA Regimen is defined as neoadjuvant IMFINZI + gem-cis followed by adjuvant IMFINZI as a single agent after RC.1

‡At the reanalysis (data cutoff: April 2024), 37.3% (n=199/533; 95% CI, 33.2-41.6) of patients treated with the NIAGARA Regimen† and 27.5% (n=146/530; 95% CI, 23.8-31.6) of patients treated with neoadjuvant gem-cis achieved a pCR.3

§Assessed with the VENTANA PD-L1 (SP263) Assay using the TC/IC25% algorithm. High PD-L1 expression was defined as ≥25% of TCs with any membrane staining, or ICs staining for PD-L1 at any intensity.5

What were the surgical data in the NIAGARA study?

Time to RC following neoadjuvant treatment was similar between treatment arms: 39 days (range: 8-118) with IMFINZI + gem-cis and 38 days (range: 12-333) with gem-cis3

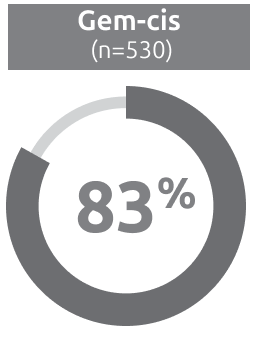
PERCENTAGE OF PATIENTS WHO UNDERWENT RC1,3

88% of Patients in the IMFINZI Plus Gem-Cis Arm Underwent Radical Cystectomy (RC).
83% of Patients in the Gem-Cis Arm Underwent Radical Cystectomy (RC).

REASONS FOR NOT UNDERGOING OR COMPLETING RC3

  The NIAGARA Regimen*
(n=533)
Neoadjuvant gem-cis
(n=530)
Patients who did not undergo surgery–no.(%) 63 (11.8%) 84 (15.8%)
Patient decision 6% 6.8%
Unfit for surgery 0.4% 1.1%
Adverse event† 1.1% 1.3%
Disease progression 1.7% 1.7%
Death 0.9% 1.5%
Study discontinuation 0.6% 2.3%
Investigator decision 0.9% 1.1%
Abandoned surgery (intra-operative) 0.2% 0%

Patient decision was the primary reason for not undergoing RC


SCROLL

The percentage of patients with an adverse reaction‡ that prevented RC was
the same across both treatment arms (0.2%)1

  • 1 patient experienced interstitial lung disease leading to cancellation of surgery in the IMFINZI + gem-cis arm1
  • 1.7% (n=9) of patients in the IMFINZI + gem-cis arm and 1.1% (n=6) of patients in the gem-cis arm experienced a surgical delay§ due to AEs3

*The NIAGARA Regimen is defined as neoadjuvant IMFINZI + gem-cis followed by adjuvant IMFINZI as a single agent after RC.1

†Adverse event: Any untoward medical occurrence associated with the use of a drug in humans, whether or not considered drug related.6

‡Adverse reaction: Any adverse event caused by a drug. Adverse reactions are a subset of all suspected adverse reactions where there is a reason to conclude that the drug caused the event.6

§Defined as occurring more than 56 days after the last dose of neoadjuvant treatment.1

What was the NIAGARA study design?

NIAGARA was the largest Phase III study in cis-eligible MIBC, with >1000 patients1,2

The FIRST FDA-APPROVED regimen to combine perioperative IO* with neoadjuvant gem-cis for the treatment of cis-eligible MIBC1,2

  • The NIAGARA study evaluated a broad population of patients. Patients with borderline renal function (CrCl ≥40 mL/min to <60 mL/min) received split-dose cisplatin1,3†

NIAGARA STUDY DESIGN: PHASE III, MULTICENTER, OPEN-LABEL STUDY1,3

NIAGARA Phase III Trial Design Comparing Neoadjuvant and Adjuvant IMFINZI Plus Gem-Cis with Standard Gem-Cis Treatment.

Key inclusion criteria

  • Cis-eligible resectable MIBC (T2-T4aN0/1M0) with transitional cell and mixed transitional cell histology
  • Planning to undergo RC
  • No prior systemic chemotherapy or IO for NMIBC or MIBC
  • ECOG PS 0 or 1
  • Life expectancy ≥12 weeks at randomization
  • CrCl of ≥40 mL/min
  • Any PD-L1 expression

Stratification factors

  • Clinical tumor stage (T2N0 vs >T2N0)
  • PD-L1 status (high vs low/negative expression)
  • Renal function (borderline [CrCl ≥40 mL/min to <60 mL/min] vs adequate [≥60 mL/min])
NIAGARA Phase III Trial Design Comparing Neoadjuvant and Adjuvant IMFINZI Plus Gem-Cis with Standard Gem-Cis Treatment.

Key exclusion criteria1:

  • Pure non-urothelial or any small cell histology
  • Primary non-bladder cancer of the urothelium

Dual primary endpoints (ITT)3:

  • Event-free survival (EFS) by BICR§||
  • Pathological complete response (pCR) rates by blinded central pathology review

Select secondary endpoints1,3:

  • Overall survival (OS)
  • Proportion of patients who underwent RC
  • Safety and tolerability

What were the baseline characteristics of the patient population studied in the NIAGARA study?

The NIAGARA study included a broad population of patients including those with variant histologies, borderline renal function, and PD-L1 low/negative expression1,3

BASELINE CHARACTERISTICS (ITT)3

Baseline characteristics The NIAGARA Regimen
(n=533)
Neoadjuvant gem-cis
(n=530)
Median age (range), years 65 (34-84) 66 (32-83)
Sex (male) 82% 82%
Race#
White
Asian
Black/other
Missing data

66%
29%
2%
3%

68%
27%
1%
4%
Region — no. (%)
Europe
Asia
North American and Australia
South America

50%
28%
12%
10%

54%
27%
12%
7%
ECOG PS score**
0
1

78%
22%

78%
22%
Current/former smoker 71% 75%
Histology type††
Urothelial carcinoma
Urothelial carcinoma with variant histology
86%
14%
83%
17%
Tumor stage††‡‡
T2N0
>T2N0

40%
60%

40%
60%
Regional lymph nodes††
N0
N1

95%
5%

94%
6%
PD-L1 expression§§
High (≥25% of tumor cells)
Low/negative

73%
27%

73%
27%
Renal function
Adequate (CrCl ≥60 mL/min)
Borderline (CrCl ≥40 to <60 mL/min)

81%
19%

81%
19%

~1 out of  7 patients treated with the NIAGARA Regimen* had UC with variant histology

19% of patients
treated with the NIAGARA Regimen* had borderline renal function (CrCl ≥40 to
<60 mL/min)

27% of patients treated with the NIAGARA Regimen* had PD-L1 low/negative expression

SCROLL

#Race was reported by the patient.

**ECOG PS scores range from 0 to 5, with higher scores indicating greater disability.

††Histologic type, tumor stage, and regional lymph-node stage were assessed by the investigator on the basis of a pathological tumor assessment of a sample obtained during transurethral resection of the bladder tumor, an examination of the patient under anesthesia after the transurethral resection of the bladder tumor, and findings on computed tomography or magnetic resonance imaging.

‡‡Tumor staging was performed according to the eighth edition of the American Joint Committee on Cancer AJCC Cancer Staging Manual.

§§Baseline samples were assessed with the Ventana PD-L1 (SP263) assay (Ventana Medical Systems) according to the TC/IC25% algorithm, in which a high expression level was defined as PD-L1 expression on at least 25% of tumor cells, at least 25% of immune cells if immune cells were present in more than 1% of the tumor area, or 100% of immune cells if immune cells were present in 1% of the tumor area.

Baseline disease characteristics were well balanced across treatment arms3

*A perioperative regimen consists of both neoadjuvant and adjuvant treatment.1

†Patients with borderline renal function (CrCl ≥ 40mL/min to <60 mL/min) received split-dose cisplatin (35 mg/m2 on Days 1 and 8 of each cycle).1,3

‡Day 1: Cisplatin 70 mg/m2, gemcitabine 1000 mg/m2; Day 8: Gemcitabine 1000 mg/m2; every 21 days for 4 cycles.1,3

§Or by CPR if a biopsy was needed for analysis of a suspected new lesion.3

||Event-free survival was defined as the time from randomization to first recurrence of disease post-RC, time to first documented progression in patients who were precluded from RC, time of expected surgery in patients who refused RC or failure to undergo RC due to residual disease, or death due to any cause, whichever occurs first.3

The NIAGARA Regimen is defined as neoadjuvant IMFINZI + gem-cis followed by adjuvant IMFINZI as a single agent after RC.1

KEY POINTS: Efficacy

The NIAGARA Regimen* significantly improved EFS and OS compared with neoadjuvant gem-cis in patients with MIBC

  • 32% REDUCTION IN RISK OF AN EVENT (progression, recurrence, death, or not undergoing RC)† with the NIAGARA Regimen* vs neoadjuvant gem-cis (HR=0.68 [95% CI, 0.56-0.82]; P<0.0001)1,3
    • Median EFS was not reached with the NIAGARA Regimen* (95% CI, NR-NR) vs 46.1 months with neoadjuvant gem-cis (95% CI, 32.2-NR)1,3
  • 25% REDUCTION IN RISK OF DEATH with the NIAGARA Regimen* vs neoadjuvant gem-cis (HR=0.75 [95% CI, 0.59-0.93]; P=0.01)1,3
    • Median OS was not reached with the NIAGARA Regimen* (95% CI, NR-NR) nor with neoadjuvant gem-cis (95% CI, NR-NR)1,3
  • The NIAGARA Regimen* was studied across a broad population of cis-eligible MIBC patients, including those with PD-L1 low/negative status, borderline renal function (CrCl ≥40 mL/min to <60 mL/min), and N1 involvement1,3
*

The NIAGARA Regimen is defined as neoadjuvant IMFINZI + gem-cis followed by adjuvant IMFINZI as a single agent after RC.1

†

Event-free survival was defined as the time from randomization to first recurrence of disease post-RC, time to first documented progression in patients who were precluded from RC, time of expected surgery in patients who refused RC or failure to undergo RC due to residual disease, or death due to any cause, whichever occurs first.3

